Silent Reflux: Connect the Symptoms With the Working Diagnosis
Silent reflux is a term used when reflux of stomach contents affecting the throat or larynx is suspected, sometimes without familiar heartburn. It is one possible explanation for selected symptoms, not a diagnosis established by throat clearing or hoarseness alone.
Ask what supports the explanation, which other causes need consideration and how treatment would be reviewed. A clear plan acknowledges uncertainty while identifying the next useful step.
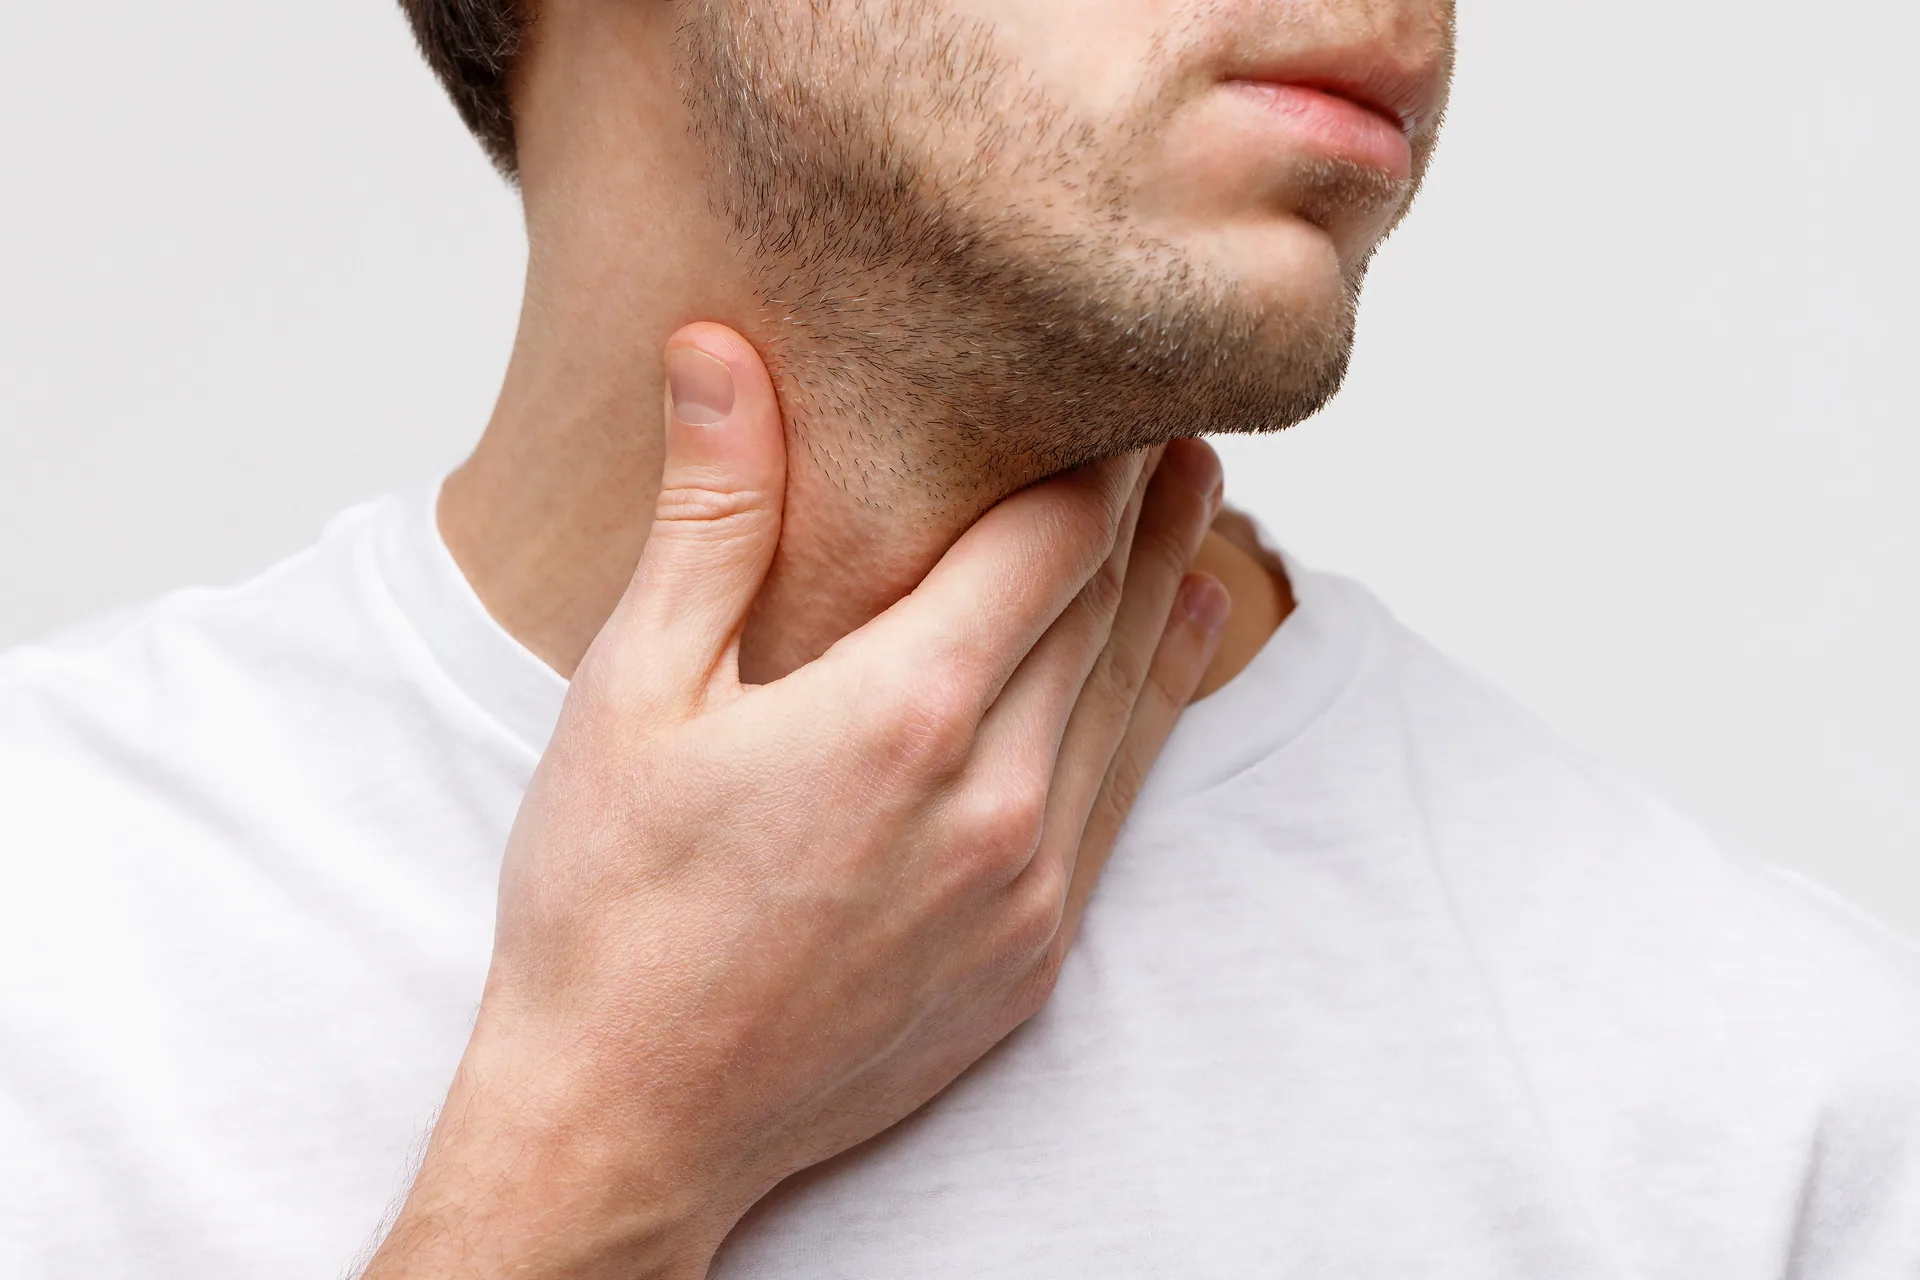
Consider the next step.
What should throat symptom assessment consider?
Throat symptom assessment should consider the timing, pattern and associated concerns, with an examination when appropriate. Nasal discharge, voice use, respiratory or digestive conditions and other factors can overlap with suspected reflux.
Explain what happens around meals, speaking or sleep and whether there is heartburn or regurgitation. Mention the symptoms even when they seem unrelated. Their absence or presence alone does not settle every diagnostic question.
Bring treatment names and describe the response. Do not assume that a medicine helping partly proves one cause or that no immediate benefit excludes every possible role.
How does assessment for throat reflux guide the plan?
Assessment for throat reflux guides the plan by identifying the evidence for the working diagnosis and the questions still unresolved. The clinician should explain whether another investigation or a review of competing causes is needed.
An irritated appearance at examination may be relevant without establishing every reason for the symptom. Ask how the history and findings fit together before committing to an indefinite treatment routine.
Laryngopharyngeal reflux without obvious heartburn
Laryngopharyngeal reflux may be discussed without obvious heartburn, but the symptom pattern remains important. Ask why the clinician considers it and what would support or weaken that explanation over time.
Suspected reflux in the throat after earlier treatment
Suspected reflux in the throat after earlier treatment should be reassessed with the actual routine and response made clear. The plan may need adjustment, another contributor may remain or the diagnosis may need reconsideration.
Lump sensation: distinguish it from food sticking
Lump sensation in the throat can occur between meals and differs from actual difficulty moving food or liquid. Tell the clinician whether swallowing is affected, which textures cause trouble and whether the problem is progressing.
Food sticking, weight loss, pain, bleeding or a neck lump should not be dismissed under a reflux label. The swallowing guide explains related assessment and safety questions.
If food remains stuck, you cannot swallow saliva or breathing is affected, seek urgent medical care. Call 000 for an emergency rather than waiting for a routine symptom review.
Voice irritation: assess the larynx and its use
Voice irritation can be described as hoarseness, effort or reduced endurance. It can have more than one cause. Explain voice demands at work or home and whether symptoms vary with use.
The voice disorders guide covers broader assessment and therapy questions. A persistent voice change may need examination rather than repeated treatment for an assumed reflux cause.
Nasendoscopy may contribute to selected assessments. It views relevant nasal and throat structures but does not examine the whole oesophagus or stomach.
Throat clearing and cough: describe the recurring pattern
Throat clearing and cough can accompany different conditions and may themselves contribute to irritation. Tell the clinician what seems to come first, whether there is a mucus sensation and how symptoms affect communication or sleep.
Do not assume a sensation of mucus proves infection or reflux. The assessment may need to consider the nose, larynx, respiratory system or other relevant factors.
Ask whether professional advice about voice use or clearing behaviour has a role. Do not copy exercises designed for a different condition without guidance.
Treatment trial: agree its purpose and intended duration
A treatment trial should have a clear purpose, instructions and review point. Advice may involve meal timing, relevant routine changes or medicines when clinically appropriate. Ask which symptom is expected to change and how soon the response can meaningfully be assessed.
Do not stop or alter prescribed medicines without discussing the plan. Equally, a trial should not become indefinite by default when the original symptoms remain unexplained.
Bedfordshire Hospitals explains the throat-related reflux discussion. Your clinician should adapt general measures to your health and the actual working diagnosis.
Suspected reflux in the throat: keep food changes practical
Suspected reflux in the throat may prompt discussion of food changes with a reason and a method for checking usefulness. Describe patterns you have noticed, then ask which adjustments are reasonable. Avoid increasingly restrictive diets based only on unconfirmed assumptions.
Nutrition concerns matter when symptoms have reduced intake or caused weight loss. Ask whether additional professional support is needed and how it fits the diagnostic plan.
Advice for reflux is not the same as advice for unsafe swallowing. If eating or drinking is difficult, obtain individual assessment rather than relying on a general list of foods to avoid.
Response review: reconsider what the trial has taught you
Response review should consider symptom changes, medicine use, tolerability and any new concern. A lack of improvement can indicate that the approach needs changing, another contributor remains or further investigation is appropriate.
Ask who reviews the trial and what information to bring. A concise record helps connect the next decision with the actual response rather than repeating a plan without learning from it.
New or worsening swallowing trouble, bleeding or other concerning changes should be reported sooner. Clinical uncertainty needs a clear review pathway rather than a confident promise from general information.
Questions about assessment for throat reflux
Does throat symptom assessment always confirm reflux?+
Throat symptom assessment does not always confirm reflux. Other contributors can produce overlapping symptoms and need consideration.
Is lump sensation the same as difficulty swallowing?+
Lump sensation is not the same as difficulty swallowing. Describe food sticking, coughing or trouble managing liquids separately so the correct questions are investigated.
Does voice irritation always need acid-suppressing medicine?+
Voice irritation does not always need acid-suppressing medicine. The findings and clinical reasoning should support the treatment recommended.
Should a treatment trial have a review date?+
A treatment trial should have a review date or clear timing instructions. Ask what response would support continuing or changing the plan.
Can response review lead to another diagnosis being considered?+
Response review can lead to another diagnosis being considered. The clinical explanation should be reconsidered when the course or findings do not fit.
Can laryngopharyngeal reflux be considered without heartburn?+
Laryngopharyngeal reflux can be considered without heartburn, but that absence does not establish the diagnosis. The wider pattern and assessment still matter.
Does suspected reflux in the throat explain every persistent cough?+
Suspected reflux in the throat does not explain every persistent cough. Other causes may need assessment according to the history and findings.
When should silent reflux symptoms be reviewed urgently?+
Silent reflux symptoms should not be used to label an urgent swallowing or breathing problem. Seek urgent care for inability to swallow saliva, food stuck or breathing difficulty.
Discuss assessment for throat reflux with the review point clear
Discuss assessment for throat reflux by asking what supports the diagnosis and how the proposed care will be evaluated. Bring earlier treatment details and report changes that do not fit the original explanation.
Start with a conversation.
Send a non-urgent enquiry about arranging a visit. Keep detailed health information and medical records for your consultation.
- 01
Tell us what brings you here
Choose an area of care and leave your contact details.
- 02
Confirm the practical details
Check the location, appointment fee and referral requirements with the practice.
- 03
Prepare for your consultation
Bring relevant reports, medicines and the questions you want to ask.